



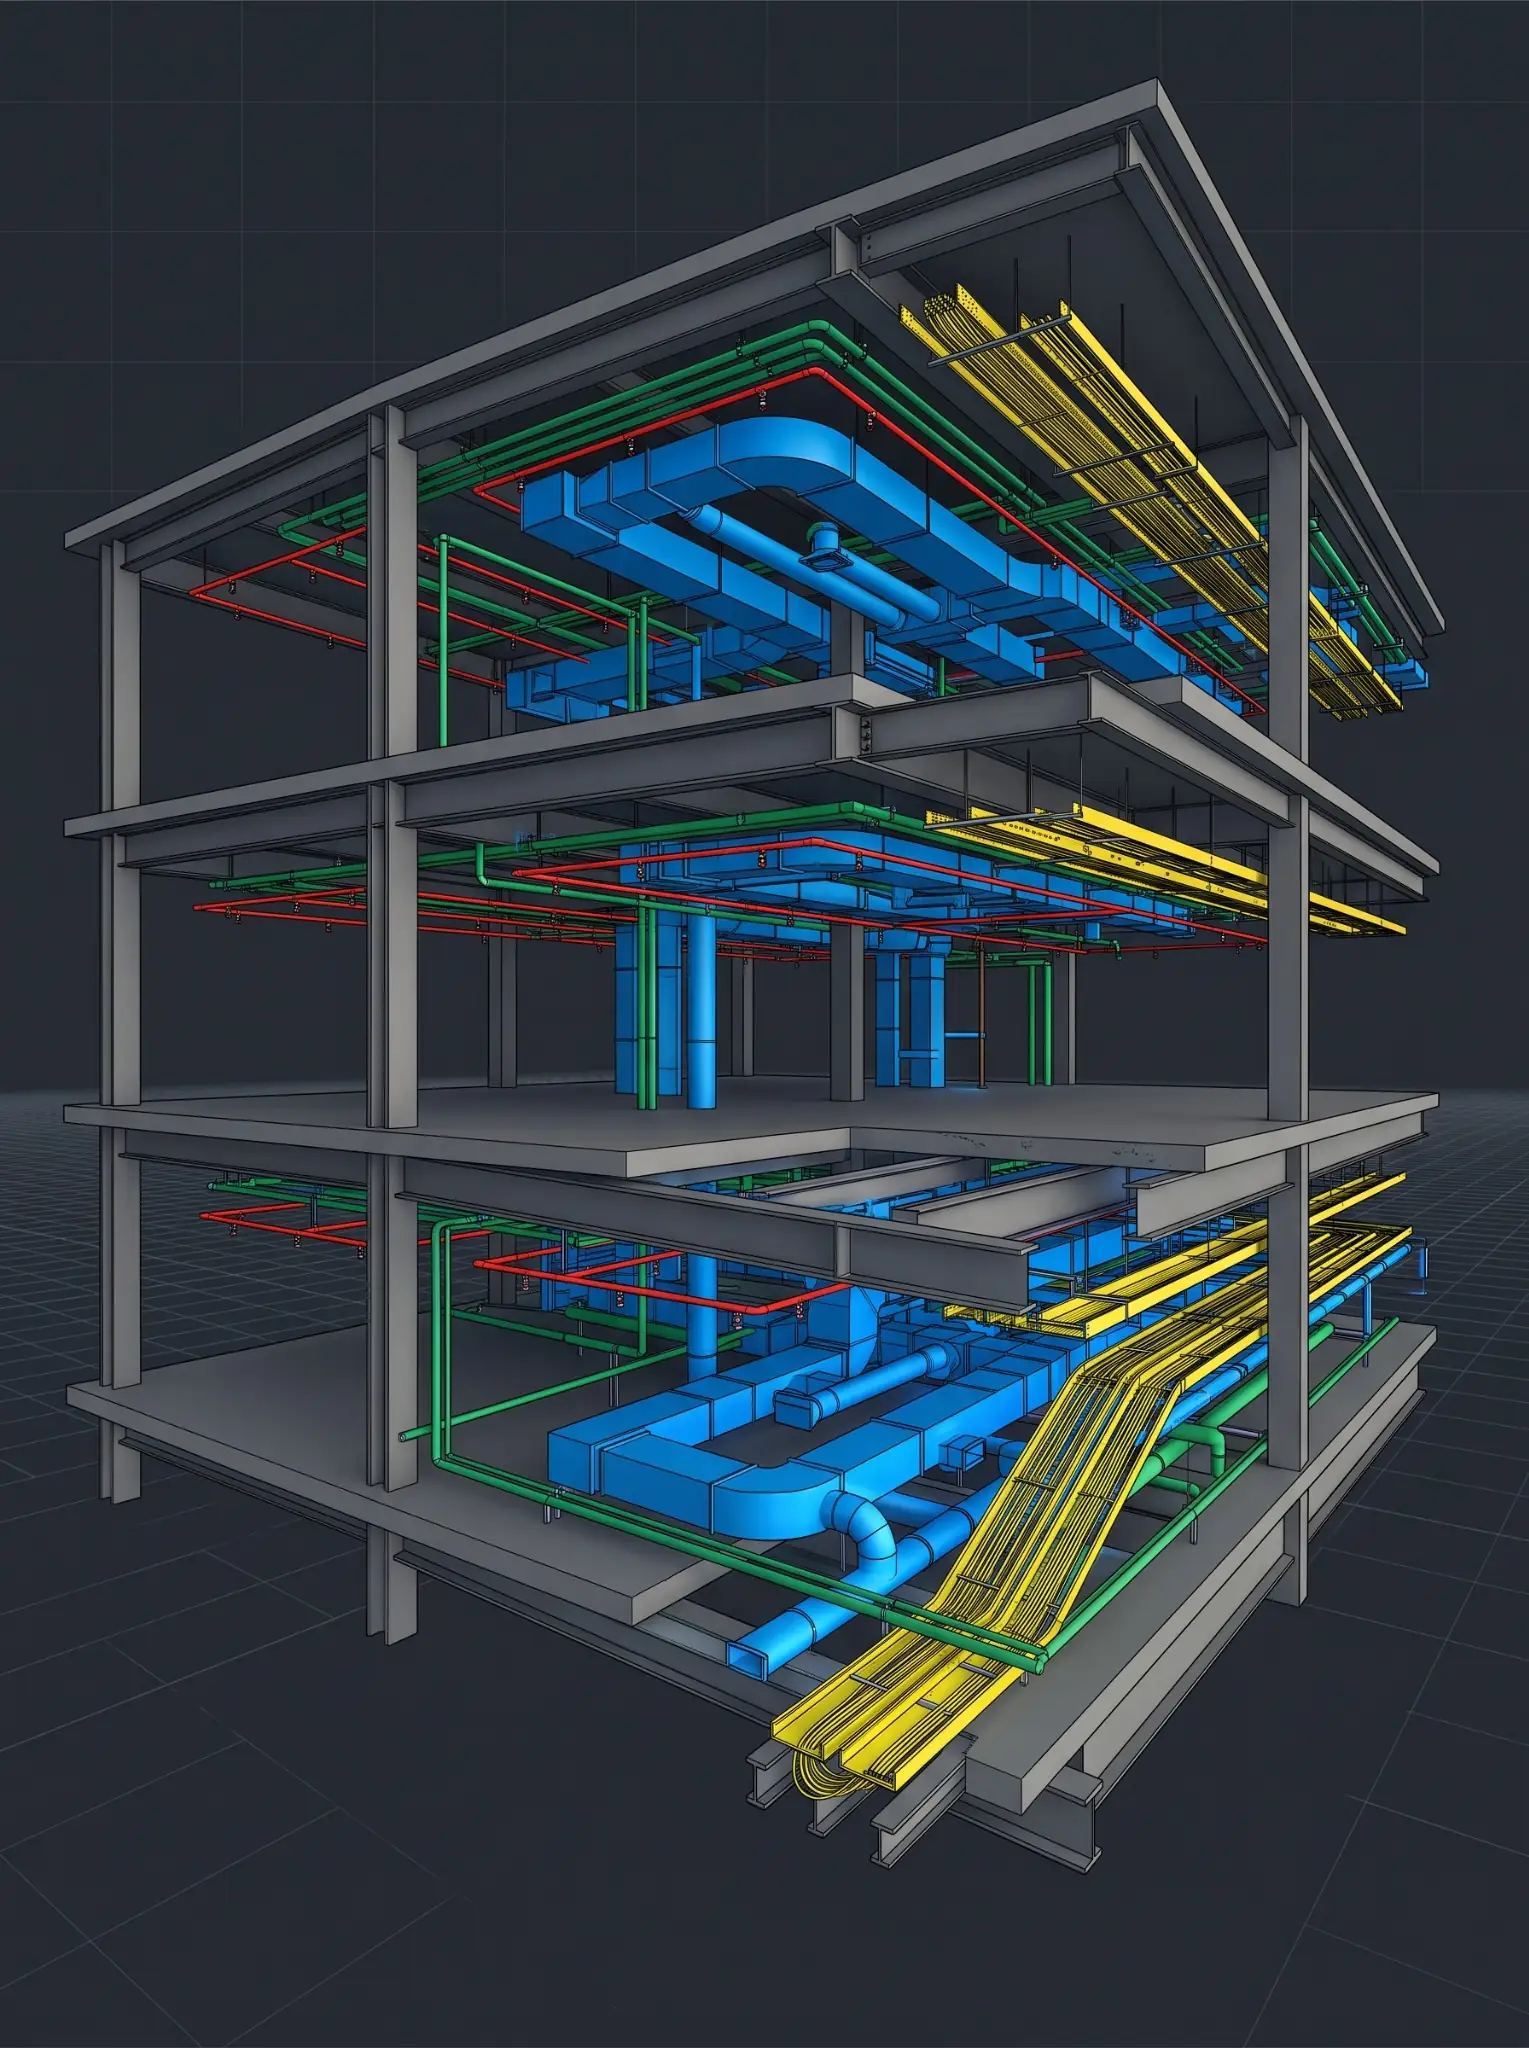









Healthcare BIM projects require a different level of discipline from a typical commercial building assignment.
A hospital, ambulatory care facility, outpatient clinic, laboratory, imaging suite, or specialty-care renovation can combine dense MEP systems, strict space constraints, equipment dependencies, infection-control requirements, occupied operations, and phased construction. A coordination issue that might be inconvenient on another project can become a patient-care, commissioning, shutdown, inspection, or schedule risk in a healthcare environment.
That is why choosing a healthcare BIM partner is not simply a question of Revit capacity or hourly cost. It is a decision about whether the delivery team can understand the project’s information requirements, work inside the owner and design team’s standards, support multidisciplinary coordination, and maintain reliable quality controls as the project evolves.
For U.S. general contractors, healthcare architects, MEP contractors, construction managers, and owners, this due-diligence checklist helps evaluate whether a BIM partner is equipped for healthcare work before active production or coordination begins.
Excelize supports BIM production, coordination, documentation, and delivery planning for complex AEC projects. For healthcare work, the team can help align BIM scope, MEP coordination, existing-condition modeling, quality checks, and delivery milestones to the operational realities of the facility and the project team.
What makes healthcare BIM coordination different?
Healthcare facilities are often MEP-dense because they must support ventilation, pressure relationships, medical gases, plumbing, power, emergency systems, low-voltage systems, controls, equipment clearances, maintenance access, and specialized clinical functions.
The BIM partner must understand that modeling is not the end goal. The goal is to support safe, buildable, coordinated information for the intended project use.
For example, healthcare ventilation design must address environmental control requirements for patient-care, resident-care, and related support areas. ANSI/ASHRAE/ASHE Standard 170 is the U.S. standard that defines minimum ventilation requirements for healthcare facilities, which is why a healthcare BIM coordination process should account for the space, system, pressure, access, and coordination needs identified by the responsible design and engineering teams.
Healthcare renovation adds another layer. Before repairs, demolition, construction, or renovation begins, the CDC recommends an infection-control risk assessment to identify exposures to dust and moisture and determine needed controls. That means the BIM team may need to coordinate not only permanent MEP systems, but also phasing, barriers, temporary conditions, access routes, shutdown constraints, and work sequencing that affect occupied areas. CDC infection-control guidance
A healthcare BIM partner does not replace the architect, engineer, infection-control team, facility manager, or contractor. The partner must be able to work inside the decisions and requirements created by those stakeholders.
Use this healthcare BIM partner scorecard
Score each prospective BIM partner from 1 to 5 for every criterion below.
- 1: Limited evidence, generic process, or meaningful delivery risk.
- 3: Relevant experience with an adequate process and project-specific discussion.
- 5: Clear healthcare-relevant proof, named delivery roles, documented QA/QC, and a credible approach to the project’s constraints.
| Evaluation area | What to evaluate | Evidence to request |
|---|---|---|
| Healthcare project relevance | Comparable facility type, MEP density, construction context, and delivery scope | Redacted project walkthrough, scope summary, team roles, and delivery method |
| MEP coordination maturity | Mechanical, electrical, plumbing, fire protection, controls, and equipment interfaces | Sample issue log, clash rules, coordination package, and responsibility matrix |
| Existing-condition capability | Renovation, occupied-facility, point-cloud, and demolition-modeling experience | Scan-to-BIM process, accuracy assumptions, sample deliverables, and source-data workflow |
| Clinical and operational constraints | Phasing, shutdowns, access, infection-control dependencies, and operational continuity | Project-specific questions, assumptions log, and coordination plan |
| Equipment and clearance awareness | Equipment rooms, imaging, central utility areas, access, maintenance, and replacement pathways | Equipment coordination checklist, clearance strategy, and modeled examples |
| Information-management discipline | BIM Execution Plan, CDE, naming, model exchange, review, and handover | Project onboarding plan and model-delivery process |
| Quality assurance | Model health, standards, parameters, drawing checks, issue closure, and review controls | QA/QC checklist, sample review log, and acceptance process |
| Team continuity | Named BIM/VDC lead, discipline reviewers, backup resources, and escalation path | Organization chart and delivery-governance plan |
| Security and access control | Role-based CDE access, confidentiality, retention, and offboarding | Access-control approach and project data-handling process |
| Commercial clarity | Scope, exclusions, revisions, deliverables, assumptions, change control, and handover | Detailed scope, commercial assumptions, and change-control method |
1. Look for comparable healthcare delivery experience
Do not settle for a general claim that the provider has worked in healthcare. Ask whether the team has delivered work comparable to your project’s actual risk profile.
A healthcare facility can vary widely in complexity. A ground-up outpatient clinic, an acute-care hospital expansion, a laboratory renovation, an imaging suite upgrade, and a central utility plant each create different coordination and information-management challenges.
Ask prospective partners to discuss relevant experience in terms of:
- Facility type.
- New construction, renovation, addition, fit-out, or phased modernization.
- Occupied versus unoccupied work areas.
- MEP system density.
- Equipment coordination needs.
- Existing-condition uncertainty.
- Trade coordination process.
- Drawing, shop-drawing, or fabrication support.
- Required model handover.
- Delivery timeline and review cycles.
The right evidence is not a set of rendered images. It is an explanation of how the team managed model inputs, coordination issues, change, quality review, and deliverables under healthcare project conditions.
Red flag: The provider can show a healthcare-looking model but cannot explain the project phase, disciplines, scope, quality process, or constraints that shaped the work.
2. Test MEP coordination, not just 3D modeling
Healthcare BIM coordination must account for more than geometry.
Mechanical, electrical, plumbing, fire protection, controls, medical-gas systems, equipment connections, supports, access zones, and service clearances can compete for limited space above ceilings, in corridors, in shafts, and in equipment rooms. The right delivery team needs a process for managing the information and decisions behind those interfaces.
Ask how the partner will handle:
- Source-model review and trade-model federation.
- Coordination priorities by system and area.
- Hard-clash, soft-clash, clearance, and access checks.
- Equipment maintenance and replacement zones.
- Required clearance information from the design team or equipment vendor.
- Issue assignment, decision tracking, and closure verification.
- Model updates after approved design or trade decisions.
- Coordination drawing or sign-off requirements.
- Drawing and model alignment before release.
Do not ask whether the team can deliver a clash-free model. That phrase is technically misleading. Clash detection identifies potential conflicts. The project team must classify issues, assign ownership, make decisions, update the model, and verify that the resulting condition is acceptable.
For a healthcare project, this process may include interfaces that require additional review by the responsible engineer, equipment planner, infection-control team, commissioning authority, or owner representative.
Excelize can support MEP coordination services through project-specific model federation, issue management, coordination workflows, QA/QC, and required drawing outputs. The scope should reflect the project’s actual trade packages and decision process.
3. Ask how the partner handles occupied renovations
An occupied healthcare renovation creates conditions that a generic BIM workflow may not address.
The BIM partner may need to model existing conditions, demolition limits, temporary routes, construction zones, ceiling work, equipment relocation, MEP shutdown boundaries, and phased releases. The purpose is not for the BIM team to make infection-control or operational decisions. The purpose is to convert project-team decisions into coordinated information that supports planning and execution.
Before selecting a partner, ask:
- How will existing conditions be captured and validated?
- What source information is available: point clouds, as-builts, site photos, surveys, facility records, or field verification?
- Who confirms discrepancies between model and field conditions?
- How will demolition, temporary work, and new work be separated?
- How will phasing be represented?
- How will the team document assumptions and unknown conditions?
- How will project-team decisions about barriers, routes, shutdowns, and access be incorporated into coordination output?
- What happens when field verification changes the routing plan?
The CDC recommends an infection-control risk assessment before construction, renovation, demolition, or repair work to define the scope and needed barrier measures. For BIM planning, that means the coordination approach should reflect the project’s infection-control and phasing decisions rather than treating the renovation as a standard new-build model. CDC environmental infection-control recommendations
For healthcare renovations, Excelize Scan to BIM services can help convert reality-capture data into usable existing-condition models, subject to agreed accuracy, source-data quality, and field-verification requirements.
Assess your healthcare BIM scope before coordination startsIf your project includes an occupied renovation, MEP-dense area, equipment upgrade, or phased care environment, Excelize can help define the model uses, source-data needs, coordination scope, delivery milestones, and quality checks before production begins.
Review Your Healthcare BIM Scope →4. Review the approach to equipment, access, and maintainability
Healthcare projects often contain equipment and systems that require more than a visual fit inside a room.
The coordination process may need to account for:
- Equipment location and connection points.
- Manufacturer-provided clearances.
- Service access and replacement pathways.
- Ceiling and wall openings.
- Structural supports.
- Medical-gas, power, controls, and plumbing interfaces.
- Access panels and maintenance zones.
- Equipment-room sequencing.
- Temporary connections or phased replacement.
The BIM partner should not invent clearance criteria. Those requirements should come from the responsible design team, equipment manufacturer, owner standards, or project documents.
What the BIM partner should do is make the requirements visible, coordinate them against other systems, identify conflicts, and maintain a clear record of decisions.
Ask to see how the provider represents access zones, clearance envelopes, equipment parameters, and coordination viewpoints. If the project includes equipment-intensive spaces, a generic clash report is not enough.
5. Check whether the partner understands healthcare ventilation constraints
Healthcare ventilation is a specialized engineering responsibility. The BIM partner does not design ventilation criteria unless it is separately contracted and properly qualified to do so.
However, the partner must be able to model, coordinate, and document the systems designed by the responsible engineers.
In healthcare facilities, ventilation requirements can influence duct size, routing, pressure relationships, filtration, air-handling configuration, terminal locations, ceiling coordination, mechanical-room layouts, and construction phasing. ASHRAE’s healthcare-facility resources identify ANSI/ASHRAE/ASHE Standard 170 as the standard that provides ventilation requirements for healthcare facilities.
Ask prospective BIM partners:
- How do you capture the design team’s required ductwork, equipment, access, and clearance criteria?
- How do you identify coordination issues affecting routing or access?
- How do you distinguish a modeling conflict from an engineering decision?
- How do you manage design changes that affect multiple systems?
- How do you prepare coordination information for review by the responsible engineer and trade team?
- How do you manage model updates after a pressure, equipment, or routing decision is approved?
The correct answer should emphasize coordination, issue visibility, and review workflow. Be cautious if a production provider implies it will independently decide engineering criteria without the appropriate project authority.
6. Require a healthcare-specific QA/QC approach
A generic BIM quality checklist may catch naming, coordinate, parameter, and model-health issues. A healthcare project requires additional project-specific checks based on its delivery scope.
For example, a healthcare BIM QA/QC plan may include:
- Verification of current architectural, structural, and MEP source inputs.
- Model coordination around critical equipment and support spaces.
- Review of required access and maintenance zones supplied by the project team.
- Checks for model-to-drawing consistency.
- Validation of parameters and data required for the project.
- Issue-log ownership and closure review.
- Revision tracking after approved RFIs or design changes.
- Review of package release status.
- Existing-condition assumptions and field-verification log.
- Final handover checks where required.
The model should be checked against the project’s intended use. A coordination model should be reviewed for coordination readiness. A fabrication model should be reviewed against the defined fabrication scope. A record model should be reviewed against record-model requirements. They are not interchangeable.
Excelize integrates QA/QC into production and coordination workflows by reviewing output against current project drawings, BIM-management requirements, agreed level of development, geometry specifications, and expected deliverables. Excelize’s BIM quality and accuracy process explains why quality controls should operate throughout delivery rather than only at final submission.
7. Check the team structure and decision workflow
A strong healthcare BIM partner has more than skilled modelers. It has a delivery structure that makes communication, review, and escalation visible.
Ask to see:
- Project manager or account lead.
- BIM/VDC manager.
- Discipline leads.
- Production team.
- QA/QC reviewer.
- Backup resources.
- Executive escalation contact.
- U.S. meeting coverage.
- Coordination meeting role.
- RFI and clarification process.
- Weekly reporting format.
- Review turnaround expectations.
For an extended delivery team, ask how the provider will maintain participation in U.S. coordination meetings and how it will handle urgent questions that could affect a release date or field decision.
Excelize can align its delivery structure with the client’s CDE, BIM Execution Plan, review cadence, and project communication plan. How Excelize works outlines the kickoff-to-handover structure that supports project-specific onboarding, quality review, delivery reporting, and coordination.
8. Make data access and handover requirements explicit
Healthcare project files may include sensitive facility information, operational layouts, equipment schedules, existing-condition data, and other information that requires controlled handling.
Before onboarding a BIM partner, define:
- Approved CDE or file-sharing environment.
- Named-user accounts and role-based permissions.
- Approved file-transfer method.
- Local download and storage rules.
- Confidentiality and data-handling requirements.
- Project data retention and deletion terms.
- Access-review and offboarding process.
- Required model and drawing handover package.
- Ownership and use rights for project-specific deliverables.
- Archive and closeout requirements.
If the project requires a record model or asset-information deliverable, define the expected fields, formats, validation process, and acceptance authority early. Do not wait until closeout to decide what final information is required.
For healthcare projects with sensitive information, apply controls proportionate to the project’s risk. ISO 19650-5 provides a security-minded information-management framework that can help project teams decide who needs access, what information needs protection, and how access should be monitored.
Build a healthcare BIM delivery plan around your project constraintsHealthcare projects require more than additional modeling capacity. They need a delivery plan that reflects MEP density, existing conditions, equipment dependencies, phased work, quality controls, file access, and handover requirements. Excelize can help you structure the scope and operating workflow before you commit to a larger program.
Plan Your Healthcare BIM Delivery →A practical healthcare BIM partner interview
Use these questions in your next partner-evaluation meeting:
- What healthcare project types have you supported, and what was your scope on each?
- How do you separate architectural, structural, MEP, equipment, and trade responsibilities?
- How do you handle incomplete existing-condition information?
- What inputs do you need before modeling begins?
- How do you manage MEP clearance, access, and equipment-interface requirements?
- How do you distinguish engineering decisions from modeling or coordination actions?
- What clash rules, issue categories, and closure process will you use?
- How do you handle active design changes, RFIs, and phased releases?
- What QA/QC checks happen before a model or drawing package reaches our team?
- Who will attend coordination meetings, and how are urgent issues escalated?
- How will you work in our CDE and comply with our access controls?
- What native files, exchange files, drawings, reports, and records will we receive at handover?
- How will you support a change in scope, partner transition, or urgent release?
- What will you report weekly to our GC, VDC, design, or trade leads?
A capable partner should answer these questions with a project-specific approach, not only a list of software tools or generic BIM capabilities.
Common healthcare BIM partner-selection mistakes
Avoid these mistakes:
- Choosing a partner based only on general healthcare portfolio images.
- Treating healthcare work as standard commercial coordination.
- Assuming a 3D model automatically captures operational, equipment, clearance, or infection-control constraints.
- Asking a BIM team to make engineering or infection-control decisions outside its assigned authority.
- Starting work before confirming existing-condition accuracy and field-verification responsibilities.
- Using a generic clash-detection scope without issue ownership or decision workflow.
- Omitting phased work, shutdowns, temporary conditions, and occupied-area constraints from the scope.
- Treating a coordination model as a fabrication model or final installation document without defined requirements.
- Deferring data security, handover, and ownership decisions until closeout.
- Selecting a partner without confirming team structure, QA/QC process, and U.S. meeting coverage.
How Excelize supports healthcare BIM delivery
Excelize helps U.S. healthcare project teams define and deliver BIM work around the realities of MEP-dense facilities, renovation conditions, coordination dependencies, and controlled information exchange.
Depending on the project scope, Excelize can support:
- Architectural, structural, and MEP modeling.
- Model federation and trade coordination.
- Clash detection and issue-management workflows.
- Existing-condition and Scan to BIM modeling.
- Coordinated drawing and shop-drawing support.
- Model QA/QC and standards alignment.
- Project-specific CDE and information-delivery workflow.
- Dedicated BIM capacity for recurring healthcare projects.
- BIM consulting for scope, standards, governance, and delivery planning.
The goal is to give the healthcare project team a controlled BIM delivery process that supports design, coordination, documentation, and project decision-making without adding unnecessary management burden.
Before selecting a partner, review Excelize BIM case studies to understand how structured BIM delivery can support complex coordination, documentation, and project-specific constraints.
Evaluate your healthcare BIM partner with greater confidenceIf you are comparing BIM providers for a hospital, clinic, laboratory, medical office, imaging suite, or occupied healthcare renovation, Excelize can help you define the evaluation criteria, sample scope, quality checks, and delivery model that fit your project.
Talk to an Excelize Healthcare BIM Expert →